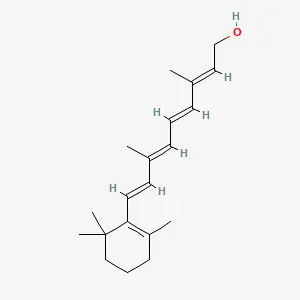
Vitamin A (retinol) is not one molecule but a family of fat-soluble compounds. The NIH (the US National Institutes of Health) calls this group retinoids, mainly retinol and retinyl esters. Your body needs them for vision, immune function, cell communication, growth and reproduction.
Retinol and its esters (preformed vitamin A) come from animal foods such as liver, fish, eggs and dairy. Plants supply provitamin A carotenoids, mainly beta-carotene, which the gut converts into vitamin A.
Here is the part most people do not know: plant sources pay out at a poor and uneven rate. The US counts 12 mcg (micrograms) of beta-carotene from food as 1 mcg RAE, the unit used for vitamin A. And 1 mcg of retinol counts as 1 mcg.
A review of human studies reports ratios from 3.8 to 1 up to 28 to 1 by weight, and common gene variants cut conversion further. So the vitamin A you get from a carrot depends on the carrot, how it is cooked and what you eat it with. It also depends on you.
Vitamin A is a nutrient with two problems. Where food is scarce, deficiency is one of the top causes of preventable blindness in children. In 2013, an estimated 29% of children aged 6 months to 5 years in 138 low- and middle-income countries were deficient.
In rich countries, frank deficiency is rare, and the risk runs the other way. Preformed vitamin A from liver and supplements can pass the upper limit (the most you should take in a day). In pregnancy, too much can cause birth defects. One 3-ounce serving of pan-fried beef liver holds 6,582 mcg RAE, more than twice the adult upper limit of 3,000 mcg.
Health benefits of vitamin A
The top findings from 35 studies, strongest evidence first
What the stars mean
- Strong. Several randomized trials, pooled in a meta-analysis, point the same way, or regulators (FDA or EFSA) have approved the claim.
- Moderate. Good randomized trials support it, but there are fewer of them, or their results vary.
- Limited. Small, short or single trials, or mixed results. Promising, but it needs confirmation.
Population and lab studies get no stars: they show a link or a mechanism, not proof.
How we rate evidence →- ★★★Fewer deaths in young childrenVitamin A supplements cut deaths from any cause by 12% in children aged 6 months to 5 years (19 trials). Vomiting in the first 48 hours was more common.
- ★★★Higher lung cancer risk in smokersIn 3 trials of supplements in smokers and asbestos workers (beta-carotene with or without retinyl palmitate), lung cancer risk was 1.10 times higher. One trial of beta-carotene plus retinol (vitamin A) found a 28% higher risk.
- ★★★No lower risk of maternal deathIn a review of 19 trials in pregnancy (over 310,000 women), vitamin A supplements alone did not change maternal deaths (four trials) or preterm birth. It did lower night blindness and anemia in mothers.
- ★★A nutrient mix slowed late macular degenerationIn people with this eye disease, multivitamins cut the odds of reaching the late stage to 0.72 times. The mix held vitamins C and E, beta-carotene and zinc, so vitamin A cannot be credited alone.
- ★★Beta-carotene pills raised death risk slightlyIn 26 trials at low risk of bias, beta-carotene raised the risk of death to 1.05 times. Vitamin A gave 1.07 times (12 trials), which could be chance, though higher vitamin A doses were linked to more deaths.
All 26 studies, strongest evidence first
The EU allows six vitamin A health claims, including vision and immunity
Regulation (EU) No 432/2012 lists a role in cell specialization and contributions to normal iron metabolism, mucous membranes, skin, vision and immune function. A food may carry these claims only if it is at least a source of vitamin A (Regulation (EC) No 1924/2006). As a rule, that means 120 µg per 100 g: 15% of the 800 µg EU Reference Intake (Regulation (EU) No 1169/2011). The wording says vitamin A contributes to these functions; it is not a treatment claim.
In young children, vitamin A cut deaths from any cause by 12%
The review covered about 1,223,856 children aged 6 months to 5 years, and 30 of its 47 studies (63%) were in Asia. In 19 trials (1,202,382 children), deaths from any cause fell to 0.88 times the risk without vitamin A (high-certainty evidence). Deaths from diarrhea fell by 12% too (0.88), and night blindness fell to 0.32 times the risk. Deaths from measles and respiratory disease did not clearly change, and vomiting in the first 48 hours was more common (1.97 times).
In pregnancy, vitamin A did not lower maternal deaths
This Cochrane review of 19 trials enrolled over 310,000 women. Against a placebo (dummy pill), vitamin A alone did not change the risk of maternal death (0.88 times; four trials, high-quality evidence). Nor did it change preterm birth (0.98). It lowered night blindness in mothers (0.79; two trials) and anemia (0.64; three studies, moderate-quality evidence). The authors note that women in the large trials in Nepal, Ghana and Bangladesh probably started with different vitamin A status.
In smokers and asbestos workers, vitamin A raised lung cancer about 10%
This Cochrane review pooled 12 trials of vitamins and minerals, 6 of them on vitamin A. In smokers or asbestos workers (3 trials, 43,995 people), vitamin A gave 1.10 times the risk of lung cancer. It gave 1.18 times the risk of lung cancer death (2 trials) and 1.09 times the risk of death from any cause (2 trials). In the general population it made little to no difference (1.09; 5 trials, 212,314 people). The smoker trials are ATBC and CARET below, which tested beta-carotene with or without retinyl palmitate.
Beta-carotene raised death risk by 5%; vitamin A had no clear effect
This review pooled 78 antioxidant trials in 296,707 people, on beta-carotene, vitamin A, vitamin C, vitamin E or selenium, often combined. In the 56 trials at low risk of bias, beta-carotene raised the risk of death to 1.05 times (26 trials). Vitamin E raised it to 1.03 times. Vitamin A gave 1.07 times the risk, a result that could be chance (12 trials), but higher vitamin A doses were linked to more deaths. The authors found no evidence to support antioxidant supplements for preventing disease.
The AREDS nutrient mix probably slows macular degeneration to its late stage
This Cochrane review covered 26 studies in 11,952 people with age-related macular degeneration (AMD), mostly the AREDS trials. AMD is an eye disease that blurs central vision. Multivitamins cut the odds of reaching late AMD to 0.72 times those on control (3 studies, 2,445 people; moderate-certainty evidence). The AREDS mix holds vitamins C and E, beta-carotene and zinc, so the result cannot be credited to vitamin A or beta-carotene alone. The review also confirmed more lung cancer with beta-carotene, mostly in former smokers, and in exploratory analyses lutein and zeaxanthin looked like a suitable replacement.
In very low birthweight babies, vitamin A slightly cut chronic lung disease
This Cochrane review had 11 trials, 10 of them (1,460 infants) comparing vitamin A with a control. Chronic lung disease (still needing oxygen) at 36 weeks was less common: 0.87 times the risk (5 studies, 986 infants). For every 11 babies treated, a case was avoided. Death or oxygen need at one month was also less common (0.93), and development at 18 to 22 months did not differ. This hospital treatment was often given as repeated, painful injections into the muscle, and it says nothing about pills for healthy people.
A vitamin A dose at birth did not lower infant deaths
In this Cochrane review of 12 trials, newborns in low- and middle-income countries got a vitamin A supplement (168,460 babies in all). For deaths by 6 months, 11 studies of all infants found no clear change (0.98 times the risk). In 3 studies of babies born at full term, the figure was 0.80, which could be chance. At 12 months it was 1.04. The authors point to conflicting results between trials and a possibly harmful effect in baby girls.
In measles, two high doses were linked to fewer deaths under 2
This Cochrane review looked at trials of vitamin A in children with measles. Across all trials, deaths did not clearly fall (0.70 times the risk). Two doses of 200,000 IU on consecutive days were linked to fewer deaths in children under 2 (0.18 times) and fewer pneumonia deaths (0.33 times). A single dose showed no benefit for deaths, and this is treatment under medical care, not routine supplementation.
In 29,133 male smokers, beta-carotene pills raised new lung cancers by 18%
In this randomized, double-blind trial, men aged 50 to 69 in southwestern Finland were assigned by chance, and nobody knew who got what. They took alpha-tocopherol (vitamin E, 50 mg a day), beta-carotene (20 mg a day), both or a placebo for 5 to 8 years. Among 876 new lung cancer cases, beta-carotene raised the rate of lung cancer by 18%, while alpha-tocopherol had no effect (-2%). Deaths from all causes were 8% higher with beta-carotene, mainly from lung cancer and ischemic heart disease (from narrowed heart arteries). The trial tested beta-carotene, not vitamin A itself.
Beta-carotene plus retinol raised lung cancer risk 28% in high-risk people
This randomized, placebo-controlled trial gave 18,314 smokers and asbestos-exposed workers 30 mg of beta-carotene plus 25,000 IU of retinol as retinyl palmitate a day. That is 7,500 mcg RAE by the NIH’s conversion. After an average of 4.0 years, lung cancer risk was 1.28 times that on placebo. Deaths from any cause were 1.17 times and lung cancer deaths 1.46 times. The trial ended 21 months early, and because it tested a mixture, the harm cannot be assigned to either part.
Six years after CARET, extra lung cancer risk was no longer clear
The same authors followed the 18,314 people of the CARET trial above for about six years after the supplements stopped, through 2001. Lung cancer risk was 1.12 times that on placebo, and death from any cause 1.08 times; both could be chance. The extra risk of cardiovascular (heart and blood vessel) deaths fell to 1.0 soon after stopping. Women had larger relative risks than men for lung cancer death (1.33 vs 1.14) and cardiovascular death (1.44 vs 0.93). The same held for death from any cause (1.37 vs 0.98).
In north India, six-monthly vitamin A did not clearly lower child deaths
About 1 million children in north India took part, in the areas served by 8,338 child-care centres, which were assigned to groups by chance. Children aged 6 to 72 months got 200,000 IU of retinyl acetate in oil every 6 months, or no vitamin A (an open control). Blood retinol rose from 0.62 to 0.72 µmol/L (micromoles per liter), and severe deficiency halved (6% vs 13%). Deaths per centre at ages 1 to 6 years were 3.01 against 3.15, a ratio of 0.96 that could be chance. Pooled with eight earlier trials, deaths were 11% lower. Roche donated the vitamin A.
In Ghanaian women, weekly vitamin A did not lower pregnancy-related deaths
This double-blind trial assigned clusters (groups of women) by chance. Women of reproductive age took weekly vitamin A (25,000 IU retinol equivalents; 104,484 women) or a placebo (103,297 women). There were 138 pregnancy-related deaths on vitamin A (348 per 100,000 pregnancies) and 148 on placebo (377 per 100,000), adjusted odds of 0.92. Deaths from all causes did not differ either (1.01). The authors said the evidence does not support vitamin A for women in safe motherhood strategies.
In rural Nepal, weekly vitamin A or beta-carotene cut pregnancy-related deaths 44%
In this double-blind trial, groups of women were assigned by chance, and 44,646 married women took part for over 3½ years. Each week, at recommended amounts, they took vitamin A (7,000 mcg retinol equivalents), beta-carotene (42 mg, equal to 7,000 mcg) or a placebo. Pregnancy-related deaths were 704 (placebo), 426 (vitamin A) and 361 (beta-carotene) per 100,000 pregnancies. Together, the two supplements gave 0.56 times the risk on placebo. The women lived in undernourished communities, and the Ghana trial did not repeat the result.
In people at risk, antioxidants plus zinc cut advanced macular degeneration odds
This placebo-controlled trial followed 3,640 people at risk of advanced macular degeneration for 6.3 years on average. Daily tablets held vitamin C (500 mg), vitamin E (400 IU) and beta-carotene (15 mg). Others held zinc (80 mg) with copper (2 mg), or both, or a placebo. Antioxidants plus zinc cut the odds of advanced disease to 0.72 times, while antioxidants alone gave 0.80, a result that could be chance. Beta-carotene was one of four active nutrients, so the result is not about vitamin A alone.
In AREDS2, dropping beta-carotene did not change macular degeneration progression
This randomized trial followed 4,203 people aged 50 to 85 at risk of advanced AMD for a median of 5 years. Adding lutein (10 mg) and zeaxanthin (2 mg), omega-3 fats, or both to the AREDS mix did not clearly slow the disease. For lutein and zeaxanthin, the risk was 0.90 times. Removing beta-carotene had no apparent effect. Lung cancers were more common with beta-carotene (23 [2.0%] vs 11 [0.9%]), mostly in former smokers. The authors said lutein and zeaxanthin could replace it.
Orange sweet potato improved a measure of vitamin A stores in schoolchildren
This randomized trial had two groups of 90 South African schoolchildren aged 5 to 10, over 53 school days. Each day the treatment group ate 125 g of boiled, mashed orange-fleshed sweet potato (1,031 retinol activity equivalents as beta-carotene, as published). The control group ate white-fleshed sweet potato, which has no beta-carotene. A vitamin A status test, the ratio of 3,4-didehydroretinol to retinol, improved more in the orange group (effect -0.008). The share with normal status rose from 78% to 87%, a change that could be chance.
In retinitis pigmentosa, high-dose vitamin A slowed the loss of retinal function
This randomized, double-masked trial followed 601 people aged 18 to 49 with this inherited eye disease for 4 to 6 years. People took 15,000 IU a day of vitamin A, 400 IU of vitamin E, or both (vitamin A plus 400 IU of vitamin E). Another group took trace amounts of both (a 2 x 2 design). A test of the retina’s cone cells (the electroretinogram) declined more slowly with vitamin A. Among 354 patients with stronger starting signals, those on vitamin A were 32% less likely to have a 50% drop in a given year. Those on vitamin E were 42% more likely. The dose is above the adult upper limit (3,000 mcg RAE, or 10,000 IU), so it belongs under medical care.
It is uncertain whether vitamin A slows retinitis pigmentosa
This Cochrane review of four trials covered 944 people aged 4 to 55, who took vitamin A, fish-oil DHA or both. The certainty of the evidence was very low. Only one trial compared vitamin A with placebo (572 people). It found a slight difference in the yearly decline of the eye test, 6.1% versus 7.1%, in favor of vitamin A. No trial showed that the vitamins helped against loss of sharp sight (visual acuity).
Added to pneumonia care in children, vitamin A did not lower deaths
This Cochrane review of five trials covered 1,453 infants and children who had pneumonia but not measles. The odds of death were not lower with vitamin A (1.49, with a wide range). The illness was more severe after high-dose vitamin A than after placebo. Low-dose vitamin A was linked to fewer repeat bouts of bronchopneumonia (0.12). Not all studies measured all outcomes, so the review may have been too small to detect differences.
Staples fortified with vitamin A and other nutrients probably reduce subclinical deficiency
This Cochrane review of 10 trials covered 4,455 people in low- and upper-middle-income countries, over 3 to 9 months. Fortifying with vitamin A alone left blood retinol little changed (0.03 µmol/L; very low-certainty evidence). Fortifying with vitamin A plus other micronutrients probably lowered subclinical deficiency (a shortfall without symptoms) to 0.27 times the risk (3 studies; moderate-certainty evidence). Six studies had a high risk of bias, and no trial reported deaths.
In pregnancy, high-dose vitamin A pills were linked to certain birth defects
In this cohort study (it followed a group over time), 22,748 pregnant women reported their diet and supplements in the first trimester. Of 339 babies with birth defects, 121 had defects in tissues from the cranial neural crest, early embryo cells that help form the head. Women taking more than 10,000 IU a day of vitamin A as supplements had 4.8 times the rate of women taking 5,000 IU or less. There seemed to be a threshold near 10,000 IU (3,000 mcg RAE by the NIH’s conversion). The excess was concentrated before the seventh week of pregnancy. These are observational data, which cannot prove cause, but animal studies point the same way.
After menopause, top vitamin A intake went with 48% more hip fractures
The Nurses’ Health Study followed 72,337 postmenopausal women for 18 years, with 603 hip fractures. Women in the highest fifth of total vitamin A intake got 3,000 mcg retinol equivalents a day or more. They had 1.48 times the risk of women in the lowest fifth (under 1,250 mcg). The link came mainly from retinol (1.89 times), while the beta-carotene result could be chance (1.22). It was weaker in women using estrogen. A 2024 review by EFSA (the EU’s food safety agency) judged that cause cannot be established below the upper limit.
In men, top blood retinol went with 2.5 times hip fracture risk
This population cohort followed 2,322 men aged 49 to 51 for 30 years, with 266 fractures. Against men in the middle fifth of blood retinol, men in the highest fifth had 1.64 times the rate of any fracture. Their rate of hip fracture was 2.47 times. Blood beta-carotene was not linked to fracture. Blood retinol is not the same as intake, and observational data cannot show cause.
Higher carotenoid levels went with less heart disease, cancer and early death
This systematic review and dose-response meta-analysis (a study that pools earlier studies) combined 69 prospective studies (99 publications) on vitamin C, carotenoids and vitamin E. Higher intake or blood levels of carotenoids went with less coronary heart disease, stroke, cardiovascular disease, cancer and death from any cause. These carotenoids included beta-carotene, alpha-carotene and beta-cryptoxanthin. The authors read this as a marker of eating fruit and vegetables. They supported eating more of them, but not taking antioxidant supplements.
Foods high in vitamin A
Food has two kinds of vitamin A. Preformed vitamin A is highest in liver, fish, eggs and dairy products, according to the NIH. Provitamin A comes from leafy greens, orange and yellow vegetables, tomato products and fruit.
In the US and other high-income countries, about 65% to 80% of the vitamin A people eat is preformed. In low-income countries, provitamin A is the main form. Fortified foods such as milk and some cereals add more.
Our USDA ranking is plant-heavy and has no organ meats. Per serving, sweet potatoes lead with 1,188 mcg RAE in one medium potato (151 g). That is 132% of the 900 mcg Daily Value, the FDA’s daily target for food labels. Carrots follow with 509 mcg in one medium carrot (61 g), then cantaloupe at 270 mcg per cup.
The ranking shows the rest, from bell peppers to eggs. Per 100 g the order changes: carrots hold 835 mcg and sweet potatoes 787 mcg. Spinach (469 mcg), parsley (421 mcg) and dill (386 mcg) come next.
The NIH table adds what our ranking lacks. Pan-fried beef liver has 6,582 mcg RAE in 3 ounces (731% of the Daily Value).
A whole baked sweet potato has 1,403 mcg, frozen boiled spinach 573 mcg per ½ cup and raw carrots 459 mcg per ½ cup. Pickled herring has 219 mcg in 3 ounces and a hard-boiled egg 75 mcg. Skim milk with added vitamin A and D has 149 mcg per cup.
Cooking can raise the amount of beta-carotene the body can use, the NIH says. In one trial, a salad with fat-free dressing gave almost no carotenoid absorption, while full-fat dressing gave the most. In another, breaking up the cell walls of spinach raised beta-carotene absorption.
A review of food science explains that light, heat and acids turn the natural trans form of carotenoids into cis forms. The main cause of loss in processing and storage is oxidation (reaction with oxygen), which depends on oxygen, light and storage conditions.
Per serving. Bars show the share of the Daily Value (900 µg a day). The line marks 100%.
Per 100 g. Bars show the share of the Daily Value (900 µg a day).
Per serving. Bars show the share of the EU Reference Intake (800 µg a day). The line marks 100%.
Per 100 g. Bars show the share of the EU Reference Intake (800 µg a day). The line marks 100%.
Per 100 kcal: the same calories of each food, for a fair comparison. Bars compare each food with the top food.
- 1.

- 2.

- 3.

- 4.

- 5.

- 6.

- 7.

- 8.

- 9.

- 10.



- 1.
- 2.
- 3.
- 4.

- 5.

- 6.
- 7.

- 8.

- 9.

- 10.



- 1.
- 2.
- 3.
- 4.
- 5.
- 6.
- 7.
- 8.
- 9.
- 10.


Sources
- FoodData Central. US Department of Agriculture, Agricultural Research Service. Values as shown in the ranking above.
- Vitamin A and carotenoids: fact sheet for health professionals. National Institutes of Health, Office of Dietary Supplements. Updated March 10, 2025.
- Brown MJ, Ferruzzi MG, Nguyen ML, et al. Carotenoid bioavailability is higher from salads ingested with full-fat than with fat-reduced salad dressings as measured with electrochemical detection. Am J Clin Nutr. 2004.
- Castenmiller JJ, West CE, Linssen JP, et al. The food matrix of spinach is a limiting factor in determining the bioavailability of beta-carotene and to a lesser extent of lutein in humans. J Nutr. 1999.
- Rodriguez-Amaya DB. Food carotenoids: analysis, composition and alterations during storage and processing of foods. Forum Nutr. 2003.
How vitamin A works
Most of this section comes from reviews, physiology studies and animal work, not from trials of vitamin A in people. Four ideas cover it.
Vitamin A is part of the light-sensing pigment of the eye, and its active form, retinoic acid, switches genes on and off. The liver stores it and releases it as needed, and the body makes it from plant pigments at a poor and uneven rate. Then comes what has been seen in people.
It is part of the light-sensing pigment of the eye
Vitamin A is an essential part of rhodopsin, the light-sensitive protein in the retina that responds to light entering the eye. It also supports the normal specialization and function of the membranes that cover the eye and the cornea, according to the NIH.
Historians trace the chemistry to George Wald and colleagues. From the 1930s, they showed that light splits rhodopsin into retinal, the aldehyde form of vitamin A, and a protein called opsin.
When vitamin A runs low, rhodopsin falls. The first sign is night blindness, the inability to see in low light. If the shortage continues, the cornea is affected (xerophthalmia, a drying of the eye), and this can end in permanent blindness.
How vitamin A supports vision. Simplified, not to scale.
Its active form switches genes on and off
Cells turn retinol into retinal and then into retinoic acid, the two main active forms in the body, according to the NIH. Retinoic acid works as a signal. A review of its biology explains that it binds retinoic acid receptors in the cell nucleus. These receptors sit on response elements near target genes and regulate their activity.
This is how vitamin A guides cells as they specialize, which is the subject of one of the EU claims. It is also how embryos form organs and limbs. Too much retinoic acid disturbs that development. That is why high intakes of preformed vitamin A in early pregnancy are teratogenic (cause birth defects), according to EFSA.
A second review describes experiments in mice and rats. In them, retinoic acid helps T cells, a part of the immune system, specialize and move into tissues. Its author notes that data from human studies are still needed.
How vitamin A can steer genes. Simplified, not to scale.
The liver stores it and releases it as needed
After a meal, liver cells take up dietary vitamin A. More than 80% of the vitamin A in the liver is stored in hepatic stellate cells, according to a review of its absorption and storage. The NIH adds that most of the body’s vitamin A is stored in the liver as retinyl esters. A carrier protein, RBP4, is needed to mobilize the stored vitamin A.
Because the liver acts as a buffer, blood retinol does not fall until liver stores are almost used up. Infections lower it too, the NIH says. So a blood test can miss low stores, and it can read low during an infection when stores are fine.
The NIH says a blood level of 20 mcg/dL (0.70 µmol/L) or less often reflects moderate deficiency. A level of 10 mcg/dL (0.35 µmol/L) or less often reflects severe deficiency. Both units describe how much is in your blood.
How the body stores and releases vitamin A. Simplified, not to scale.
It is made from plant pigments at a poor, uneven rate
The gut enzyme BCMO1 converts provitamin A carotenoids such as beta-carotene into vitamin A. The NIH says the body may absorb 75% to 100% of retinol but, in most cases, only 10% to 30% of beta-carotene from foods. That is why units differ by source.
In the US, 1 mcg RAE equals 1 mcg of retinol or 2 mcg of beta-carotene from supplements. It also equals 12 mcg of beta-carotene from food, or 24 mcg of alpha-carotene or beta-cryptoxanthin. EFSA still counts 6 mcg of beta-carotene (and 12 mcg of other provitamin A carotenoids) as 1 mcg retinol equivalent. That is why EU and US numbers are not the same size.
Human trials found ratios that vary with the food, the dose, the method and the person, as the chart shows.
A review of the human evidence puts absorption of beta-carotene from plants at 5% to 65%. It puts the ratios at 3.8 to 1 up to 28 to 1. They depend on the food matrix (the food’s structure), the processing and the fat and fiber in the diet, the review says. The person’s own status and genes matter too.
Micrograms of beta-carotene needed for 1 microgram of retinol, drawn to scale. Shorter is better. The studies used different foods, methods and people.
What has been seen in people
The human findings match the mechanisms best where vitamin A is short. In deficient populations, supplements restored stores and cut night blindness (0.32 times the risk in children, 0.79 in pregnant women). They also lowered child deaths by 12%.
Where status is already adequate, extra vitamin A showed no clear benefit. Large doses of beta-carotene, with or without retinyl palmitate, harmed smokers. The gene and immune findings above come from lab and animal work, and the human trials do not test them directly. All the trials are among the study cards above.
Sources
- Vitamin A and carotenoids: fact sheet for health professionals. National Institutes of Health, Office of Dietary Supplements. Updated March 10, 2025.
- EFSA Panel on Nutrition, Novel Foods and Food Allergens (NDA). Scientific opinion on the tolerable upper intake level for preformed vitamin A and β-carotene. EFSA J. 2024.
- European Commission. Regulation (EU) No 432/2012 establishing a list of permitted health claims made on foods. 2012.
- Imdad A, Mayo-Wilson E, Haykal MR, et al. Vitamin A supplementation for preventing morbidity and mortality in children from six months to five years of age. Cochrane Database Syst Rev. 2022.
- McCauley ME, van den Broek N, Dou L, et al. Vitamin A supplementation during pregnancy for maternal and newborn outcomes. Cochrane Database Syst Rev. 2015.
- Lanska DJ. Chapter 29: historical aspects of the major neurological vitamin deficiency disorders: overview and fat-soluble vitamin A. Handb Clin Neurol. 2010.
- Cunningham TJ, Duester G. Mechanisms of retinoic acid signalling and its roles in organ and limb development. Nat Rev Mol Cell Biol. 2015.
- Ross AC. Vitamin A and retinoic acid in T cell-related immunity. Am J Clin Nutr. 2012.
- Blaner WS, Li Y, Brun PJ, et al. Vitamin A Absorption, Storage and Mobilization. Subcell Biochem. 2016.
- Tanumihardjo SA, Russell RM, Stephensen CB, et al. Biomarkers of Nutrition for Development (BOND)-Vitamin A Review. J Nutr. 2016.
- Haskell MJ. The challenge to reach nutritional adequacy for vitamin A: β-carotene bioavailability and conversion–evidence in humans. Am J Clin Nutr. 2012.
- Haskell MJ, Jamil KM, Hassan F, et al. Daily consumption of Indian spinach (Basella alba) or sweet potatoes has a positive effect on total-body vitamin A stores in Bangladeshi men. Am J Clin Nutr. 2004.
- de Pee S, West CE, Permaesih D, et al. Orange fruit is more effective than are dark-green, leafy vegetables in increasing serum concentrations of retinol and beta-carotene in schoolchildren in Indonesia. Am J Clin Nutr. 1998.
- Tang G, Qin J, Dolnikowski GG, et al. Spinach or carrots can supply significant amounts of vitamin A as assessed by feeding with intrinsically deuterated vegetables. Am J Clin Nutr. 2005.
- Gannon B, Kaliwile C, Arscott SA, et al. Biofortified orange maize is as efficacious as a vitamin A supplement in Zambian children even in the presence of high liver reserves of vitamin A: a community-based, randomized placebo-controlled trial. Am J Clin Nutr. 2014.
How much vitamin A do you need?
Adult men need 900 mcg RAE of vitamin A a day and adult women 700 mcg RAE. These are the US recommended dietary allowances (RDAs), amounts that cover nearly all healthy people. EFSA’s population reference intakes in the EU are 750 mcg RE for men and 650 mcg RE for women.
RAE (retinol activity equivalents) account for how well each form turns into vitamin A. RE (retinol equivalents) is the older EU unit with a different beta-carotene factor, so the two are not the same size. On older labels, 1 IU of retinol equals 0.3 mcg RAE. So the 900 mcg RAE allowance is 3,000 IU of retinol, or 18,000 IU of beta-carotene from food, according to the NIH.
Needs rise in pregnancy and breastfeeding. The US allowance is 770 mcg RAE a day in pregnancy at ages 19 to 50 (750 mcg at ages 14 to 18). When breastfeeding it is 1,300 mcg RAE (1,200 mcg at ages 14 to 18).
EFSA sets 700 mcg RE in pregnancy. That covers about 51 mcg RE a day more for the growing baby in the second half of pregnancy. EFSA sets 1,300 mcg RE when breastfeeding, to replace the retinol lost in milk.
For older adults, the US allowance stays at 900 mcg RAE for men and 700 mcg RAE for women from age 51. Children need 300 mcg RAE at ages 1 to 3, 400 mcg at ages 4 to 8 and 600 mcg at ages 9 to 13.
The NIH notes that people with cystic fibrosis get lifelong vitamin A as part of standard care. They take 750 to 3,000 mcg RAE a day, depending on age. EFSA advises smokers to avoid beta-carotene supplements.
According to the NIH, average US intakes from foods and drinks in 2017 to 2018 were 682 mcg RAE for men. Women got 616 mcg. In 2003 to 2006 survey data, fewer than 1% of Americans had a blood retinol below 20 mcg/dL, so frank deficiency is uncommon there.
Vitamin A: recommended intake per day
US: Adequate Intake / Recommended Dietary Allowance (NASEM). EU: Population Reference Intake (EFSA).
| Age and sex | US (RDA) | EU (PRI) |
|---|---|---|
| Men, 31–50 years | 900 µg RAE | 750 µg RE |
| Women, 31–50 years | 700 µg RAE | 650 µg RE |
All ages, pregnancy and breastfeeding
| Age and sex | US (AI/RDA) | EU (PRI) |
|---|---|---|
| Infants 0–6 months | 400 µg RAE | None set |
| Infants 7–11 months | None set | 250 µg RE |
| Infants 7–12 months | 500 µg RAE | None set |
| Children 1–3 years | 300 µg RAE | 250 µg RE |
| Children 4–6 years | None set | 300 µg RE |
| Children 4–8 years | 400 µg RAE | None set |
| Children 7–10 years | None set | 400 µg RE |
| Females 9–13 years | 600 µg RAE | None set |
| Males 9–13 years | 600 µg RAE | None set |
| Children 11–14 years | None set | 600 µg RE |
| Females 14–18 years | 700 µg RAE | None set |
| Males 14–18 years | 900 µg RAE | None set |
| Children 15–17 years, female | None set | 650 µg RE |
| Children 15–17 years, male | None set | 750 µg RE |
| Adults 18+ years, female | None set | 650 µg RE |
| Adults 18+ years, male | None set | 750 µg RE |
| Females 19–30 years | 700 µg RAE | None set |
| Males 19–30 years | 900 µg RAE | None set |
| Females 31–50 years | 700 µg RAE | None set |
| Males 31–50 years | 900 µg RAE | None set |
| Females 51–70 years | 700 µg RAE | None set |
| Males 51–70 years | 900 µg RAE | None set |
| Females >70 years | 700 µg RAE | None set |
| Males >70 years | 900 µg RAE | None set |
| Pregnancy 14–18 years | 750 µg RAE | None set |
| Pregnancy | None set | 700 µg RE |
| Pregnancy 19–30 years | 770 µg RAE | None set |
| Pregnancy 31–50 years | 770 µg RAE | None set |
| Lactation 14–18 years | 1,200 µg RAE | None set |
| Lactation | None set | 1,300 µg RE |
| Lactation 19–30 years | 1,300 µg RAE | None set |
| Lactation 31–50 years | 1,300 µg RAE | None set |
EU and US age bands differ; "None set" means that body sets no value for the group. Label reference: FDA Daily Value 900 µg, EU Reference Intake 800 µg.EU and US age bands differ; "None set" means that body sets no value for the group. Label reference: EU Reference Intake 800 µg, FDA Daily Value 900 µg.
Vitamin A deficiency: signs and who is at risk
The first sign is night blindness, trouble seeing in low light. Later the cornea is affected (xerophthalmia), and left untreated it can cause permanent blindness. The NIH calls vitamin A deficiency one of the top causes of preventable blindness in children.
Chronic deficiency also makes infections, especially measles and diarrhea, more severe and more deadly. It is linked to abnormal lung development, anemia and death. Bitot’s spots, another eye sign, fell by about half with supplements in the Cochrane review of children (0.42 times the risk).
Deficiency is common where diets lack both animal foods and orange or green plant foods. An analysis of surveys looked at children aged 6 months to 5 years in 138 low- and middle-income countries. In 2013, 29% were deficient (blood retinol below 0.70 µmol/L).
Rates were highest in sub-Saharan Africa (48%) and south Asia (44%). Deficiency was linked to 94,500 deaths from diarrhea and 11,200 from measles that year.
In richer countries, premature infants are most at risk, according to the NIH, because they have low liver stores at birth. So are people who absorb fat poorly. Up to 90% of people with cystic fibrosis have pancreatic insufficiency (the pancreas makes too few digestive enzymes). About one quarter of children with Crohn’s disease and ulcerative colitis are deficient, and so are some people with newly diagnosed celiac disease.
Testing is harder than it sounds. Doctors usually measure blood retinol, but it does not fall until liver stores are nearly gone. A low reading can also come from infection or inflammation, because the carrier protein drops during inflammation. Liver stores give the best answer, but researchers can only estimate them indirectly, with isotope or dose-response tests.
Sources
- Vitamin A and carotenoids: fact sheet for health professionals. National Institutes of Health, Office of Dietary Supplements. Updated March 10, 2025.
- Institute of Medicine, Food and Nutrition Board. Dietary Reference Intakes for vitamin A, vitamin K, arsenic, boron, chromium, copper, iodine, iron, manganese, molybdenum, nickel, silicon, vanadium, and zinc. National Academy Press. 2001.
- EFSA Panel on Nutrition, Novel Foods and Food Allergens (NDA). Scientific opinion on the tolerable upper intake level for preformed vitamin A and β-carotene. EFSA J. 2024.
- Stevens GA, Bennett JE, Hennocq Q, et al. Trends and mortality effects of vitamin A deficiency in children in 138 low-income and middle-income countries between 1991 and 2013: a pooled analysis of population-based surveys. Lancet Glob Health. 2015.
- Tanumihardjo SA, Russell RM, Stephensen CB, et al. Biomarkers of Nutrition for Development (BOND)-Vitamin A Review. J Nutr. 2016.
- Imdad A, Mayo-Wilson E, Haykal MR, et al. Vitamin A supplementation for preventing morbidity and mortality in children from six months to five years of age. Cochrane Database Syst Rev. 2022.
Forms of vitamin A: absorption and effects
Supplements and fortified foods use different forms of vitamin A. Stand-alone pills and multivitamins often contain retinyl acetate, retinyl palmitate, beta-carotene or a combination, according to the NIH. Amounts vary widely: 3,000 mcg RAE is common in a stand-alone pill, and multivitamins often have 750 to 1,050 mcg RAE.
The upper limit covers only the retinol part. So if a label says 3,000 mcg RAE and 60% of it is beta-carotene, only the other 40% (1,200 mcg RAE) counts toward it.
The honest bottom line: the best comparisons measure vitamin A stores or blood markers, not health outcomes, and most are small. Preformed vitamin A and beta-carotene both raised vitamin A status in the trials we found, with beta-carotene needing a larger dose.
Beta-carotene pills carried a specific risk for smokers in the ATBC and CARET trials. EFSA found no indication that beta-carotene from the background diet is linked to harm.
We found no human trial that compared retinyl acetate with retinyl palmitate, and none that compared natural with synthetic vitamin A. In the benefits section, DEVTA used retinyl acetate in oil and CARET used retinyl palmitate with beta-carotene. ATBC and AREDS used beta-carotene, and Berson used vitamin A of unstated form.
| Form | Activity or conversion | What studies show | Source |
|---|---|---|---|
| Retinol and retinyl esters (acetate, palmitate) | 1 mcg retinol = 1 mcg RAE | The NIH puts absorption of retinyl esters from supplements at 70% to 90% and of retinol from food at up to 75% to 100%. In Bangladeshi men, retinyl palmitate raised vitamin A stores by 0.065 mmol, about the same as synthetic beta-carotene (0.062 mmol). Weekly preformed vitamin A cut night blindness in pregnant women in Nepal more than beta-carotene did. EFSA’s upper level covers retinol, retinyl acetate and retinyl palmitate. We found no human trial comparing acetate with palmitate. | 1, 2, 3, 4 |
| Water-miscible, emulsified or solid retinol | Not stated | In a review of 259 case reports, these forms caused chronic toxicity at doses about 10 times lower than oil-based forms (0.2 mg versus 2 mg of retinol per kg of body weight a day). The authors recommend careful consideration before using them in supplements and fortification. Case reports, not a trial. | 12 |
| Beta-carotene supplements | US: 2 mcg = 1 mcg RAE. EU: 6 mcg = 1 mcg RE | The NIH puts absorption from supplements at 8.7% to 65%. In Bangladeshi men the ratio was about 6 to 1. In Nepal weekly beta-carotene cut pregnancy deaths by 49%, against 40% for vitamin A. ATBC and CARET found more lung cancer in smokers. EFSA set no upper level and advises smokers to avoid beta-carotene supplements. Long-term excess can turn the skin yellow-orange, which is harmless and reversible, according to the NIH. | 1, 2, 3, 5, 14, 15, 4 |
| Beta-carotene in food | US: 12 mcg = 1 mcg RAE. EU: 6 mcg = 1 mcg RE | Trials found about 10 to 26 mcg of beta-carotene per 1 mcg of retinol, depending on the food: orange maize 10.4, orange fruit 12, sweet potato 13, carrots 14.8, spinach 20.9 and leafy greens with carrots 26. Fat in the meal and breaking up the leaf raised carotenoid absorption. A review gives 3.8 to 1 up to 28 to 1. | 3, 6, 8, 9, 10, 11, 17 |
| Other provitamin A carotenoids (alpha-carotene, beta-cryptoxanthin) | US: 24 mcg = 1 mcg RAE. EU: 12 mcg = 1 mcg RE | These factors come from the NIH and EFSA. We found no trial that tested these carotenoids as separate supplements. | 1, 2 |
| Biofortified orange crops | Orange maize: 10.4 mcg beta-carotene equivalents = 1 mcg retinol | Orange maize raised vitamin A stores about as much as a daily vitamin A supplement in Zambian children. Orange-fleshed sweet potato improved a vitamin A status test in South African schoolchildren. | 6, 7 |
| Multivitamins and fortified foods | Mixed forms: read the label | The NIH says multivitamins often have 750 to 1,050 mcg RAE. A Cochrane review found staple foods fortified with vitamin A alone left blood retinol little changed (very low certainty), while vitamin A with other nutrients probably lowered subclinical deficiency. | 1, 16 |
Here are the head-to-head and form-specific studies, strongest evidence first, 9 in all.
All 9 studies, strongest evidence first
In pregnancy, preformed vitamin A cut night blindness more than beta-carotene
In this trial in the rural plains of Nepal, 171 wards with about 29,000 women were assigned to groups by chance. For about 3 years, the women took a weekly 7,000 mcg retinol equivalents as preformed vitamin A or beta-carotene, or a placebo. They had 9,932 first pregnancies in that time. Night blindness in pregnancy fell from 10.7% on placebo to 6.7% with vitamin A (0.62 times the risk). With beta-carotene it was 0.83 times, which could be chance. In the first 3 months after birth, the figures were 0.38 (vitamin A) and 0.77 (beta-carotene). This looks like the same Nepal trial as the pregnancy deaths result above (same research group, weekly dose and setting), here looking at night blindness.
Orange maize raised vitamin A stores about as much as a supplement
This randomized, placebo-controlled trial ran for 90 days in 140 Zambian children. Each day they got white maize with placebo oil, orange maize, or white maize plus 400 mcg RAE of vitamin A in oil. Total body vitamin A stores changed by a median of 13 µmol with placebo, 84 with orange maize and 98 with the vitamin A oil. The last two did not clearly differ. The calculated conversion was 10.4 µg of beta-carotene equivalents per 1 µg of retinol. Many children already had high liver stores (59% above 1 µmol/g, which the authors call the subtoxicity cutoff).
Orange fruit raised blood retinol more than leafy vegetables and carrots
This randomized trial gave 238 anemic Indonesian schoolchildren (short of red blood cells), aged 7 to 11, two meals a day for 9 weeks. Daily, groups got 556 retinol equivalents (RE) from retinol-rich food or 509 RE from orange fruit. Others got 684 RE from dark-green leafy vegetables and carrots, or 44 RE. Blood retinol rose 0.23 µmol/L with retinol-rich food, 0.12 with fruit, 0.07 with vegetables and 0.00 in the low group. The authors estimated 12 µg of beta-carotene per RE from fruit and 26 µg from leafy vegetables and carrots.
In Bangladeshi men, synthetic beta-carotene was worth about 6 to 1
In this trial, 14 men per group ate a low-vitamin A diet (about 200 mcg RE a day) for 60 days. On top, they got 750 mcg retinol equivalents a day as cooked, pureed sweet potato, pureed Indian spinach, retinyl palmitate or synthetic beta-carotene. Total-body vitamin A stores, measured by deuterated-retinol dilution (a tracer test), rose 0.065 mmol with retinyl palmitate and 0.062 with beta-carotene. They rose 0.041 with Indian spinach and 0.029 with sweet potato, a result that could be chance. Against retinyl palmitate, Indian spinach was worth about 10 to 1 and sweet potato 13 to 1. The ratios are beta-carotene to retinol by weight.
Breaking up spinach leaves raised beta-carotene absorption from about 5.1% to 9.5%
In this three-week trial, 10 people ate a control diet and 12 per group ate one of four spinach products. These were whole leaf, minced, liquefied with enzymes, or liquefied with added fiber. Beta-carotene absorption was measured against a carotenoid supplement (relative bioavailability). It was 5.1% for whole leaf, 6.4% for minced, 9.5% for liquefied and 9.3% with added fiber. Lutein was absorbed much better (45% to 55%), and blood retinol also rose with spinach.
Labeled carrots converted about 15 to 1, spinach about 21 to 1
Seven men ate pureed spinach (300 g) or carrots (100 g) four months apart, and seven women ate spinach. All the vegetables were grown to carry a deuterium label (a traceable form of hydrogen). A week later, a reference dose of labeled retinyl acetate in oil was given for comparison. By weight, conversion to retinol was 20.9 to 1 for spinach (range 10.0 to 46.5) and 14.8 to 1 for carrots (range 7.7 to 24.5). The authors concluded that both give a meaningful amount of vitamin A, though less than once proposed; this was a very small study.
Fat-free dressing: almost no carotenoids absorbed; full-fat dressing gave the most
Seven people each ate three salads of spinach, romaine lettuce, cherry tomatoes and carrots, at least 2 weeks apart. The dressings held 0, 6 or 28 g of canola oil, and blood was drawn hourly for 12 hours. Alpha-carotene and beta-carotene barely appeared in blood fat particles with the fat-free dressing. They appeared more with the reduced-fat dressing and more again with the full-fat dressing. The study measured carotenoid absorption, not vitamin A itself.
Two common gene variants cut beta-carotene conversion 32% to 69% in women
The enzyme that splits beta-carotene is BCMO1. Two common variants, R267S and A379V, occur in 42% and 24% of gene copies (allele frequencies). After a large test dose of beta-carotene, carriers of 379V and of both variants had retinyl palmitate to beta-carotene ratios 32% and 69% lower. Their fasting beta-carotene was 160% and 240% higher. In the lab, the double mutant had 57% lower enzyme activity, which may help explain why some people convert plant pigment poorly.
Non-oil retinol forms were about 10 times as toxic as oil-based ones
This meta-analysis pooled 259 published case reports of retinol toxicity. Chronic poisoning (hypervitaminosis A) followed daily doses of 2 mg retinol per kg of body weight in oil-based products over many months or years. In water-miscible (mixes with water), emulsified or solid products, doses as low as 0.2 mg per kg for a few weeks caused it. The authors put the safe upper single dose of retinol in oil or liver at about 4 to 6 mg per kg. Case reports cannot show how common this is.
Sources
- Vitamin A and carotenoids: fact sheet for health professionals. National Institutes of Health, Office of Dietary Supplements. Updated March 10, 2025.
- EFSA Panel on Nutrition, Novel Foods and Food Allergens (NDA). Scientific opinion on the tolerable upper intake level for preformed vitamin A and β-carotene. EFSA J. 2024.
- Haskell MJ, Jamil KM, Hassan F, et al. Daily consumption of Indian spinach (Basella alba) or sweet potatoes has a positive effect on total-body vitamin A stores in Bangladeshi men. Am J Clin Nutr. 2004.
- Christian P, West KP Jr, Khatry SK, et al. Vitamin A or beta-carotene supplementation reduces but does not eliminate maternal night blindness in Nepal. J Nutr. 1998.
- West KP Jr, Katz J, Khatry SK, et al. Double blind, cluster randomised trial of low dose supplementation with vitamin A or beta carotene on mortality related to pregnancy in Nepal. The NNIPS-2 Study Group. BMJ. 1999.
- Gannon B, Kaliwile C, Arscott SA, et al. Biofortified orange maize is as efficacious as a vitamin A supplement in Zambian children even in the presence of high liver reserves of vitamin A: a community-based, randomized placebo-controlled trial. Am J Clin Nutr. 2014.
- van Jaarsveld PJ, Faber M, Tanumihardjo SA, et al. Beta-carotene-rich orange-fleshed sweet potato improves the vitamin A status of primary school children assessed with the modified-relative-dose-response test. Am J Clin Nutr. 2005.
- de Pee S, West CE, Permaesih D, et al. Orange fruit is more effective than are dark-green, leafy vegetables in increasing serum concentrations of retinol and beta-carotene in schoolchildren in Indonesia. Am J Clin Nutr. 1998.
- Tang G, Qin J, Dolnikowski GG, et al. Spinach or carrots can supply significant amounts of vitamin A as assessed by feeding with intrinsically deuterated vegetables. Am J Clin Nutr. 2005.
- Castenmiller JJ, West CE, Linssen JP, et al. The food matrix of spinach is a limiting factor in determining the bioavailability of beta-carotene and to a lesser extent of lutein in humans. J Nutr. 1999.
- Brown MJ, Ferruzzi MG, Nguyen ML, et al. Carotenoid bioavailability is higher from salads ingested with full-fat than with fat-reduced salad dressings as measured with electrochemical detection. Am J Clin Nutr. 2004.
- Myhre AM, Carlsen MH, Bøhn SK, et al. Water-miscible, emulsified, and solid forms of retinol supplements are more toxic than oil-based preparations. Am J Clin Nutr. 2003.
- Leung WC, Hessel S, Méplan C, et al. Two common single nucleotide polymorphisms in the gene encoding beta-carotene 15,15′-monoxygenase alter beta-carotene metabolism in female volunteers. FASEB J. 2009.
- Omenn GS, Goodman GE, Thornquist MD, et al. Effects of a combination of beta carotene and vitamin A on lung cancer and cardiovascular disease. N Engl J Med. 1996.
- Alpha-Tocopherol, Beta Carotene Cancer Prevention Study Group. The effect of vitamin E and beta carotene on the incidence of lung cancer and other cancers in male smokers. N Engl J Med. 1994.
- Hombali AS, Solon JA, Venkatesh BT, et al. Fortification of staple foods with vitamin A for vitamin A deficiency. Cochrane Database Syst Rev. 2019.
- Haskell MJ. The challenge to reach nutritional adequacy for vitamin A: β-carotene bioavailability and conversion–evidence in humans. Am J Clin Nutr. 2012.
Is vitamin A safe? Supplements, dose and interactions
Carotenoids from plant foods do not cause vitamin A toxicity, but preformed vitamin A from liver and supplements can. For preformed vitamin A, the US tolerable upper intake level (UL) is 3,000 mcg a day for adults, including during pregnancy and breastfeeding. The UL is the highest daily intake unlikely to cause harm.
It is 2,800 mcg at ages 14 to 18 and 1,700 mcg at ages 9 to 13. It is 900 mcg at ages 4 to 8 and 600 mcg at ages 1 to 3. It applies to animal foods and to supplements whose vitamin A comes from retinol or its esters, not to beta-carotene.
For beta-carotene the US panel set no UL, but it advises against supplements for the general population except as a source of vitamin A.
EFSA’s 2024 opinion keeps a UL of 3,000 mcg RE for adults, including women who may become pregnant, and for pregnant, breastfeeding and postmenopausal women. For children, it is 600 mcg for infants 4 to 11 months and 800 mcg at ages 1 to 3. It rises to 1,100 mcg at 4 to 6 and 1,500 mcg at 7 to 10. It is 2,000 mcg at 11 to 14 and 2,600 mcg at 15 to 17.
EFSA’s limit counts all sources, including fortified foods, and covers retinol, retinyl acetate and retinyl palmitate. It was set on birth defects, which EFSA says are irreversible and occur at relatively low intakes.
- Too much. One or a few very high doses can cause severe headache, blurred vision, nausea, dizziness, aching muscles and poor coordination. Such doses are typically more than 100 times the allowance. In severe cases they can cause coma and death. Regular high doses can cause dry skin, painful muscles and joints, fatigue, depression and abnormal liver tests, according to the NIH. Water-miscible and solid forms were far more toxic than oil-based ones in case reports. In young children, a high dose caused more vomiting in the first 48 hours (1.97 times the risk).
- Pregnancy and liver. Intakes of preformed vitamin A above the UL can cause birth defects of the eye, skull, lungs and heart, according to the NIH. In one cohort, the rate of certain defects was 4.8 times higher at more than 10,000 IU a day of supplemental vitamin A. EFSA advises women who are pregnant or planning to be not to eat liver products. It says the UL is unlikely to be exceeded if liver and offal are eaten once a month or less. A 3-ounce serving of pan-fried beef liver has 6,582 mcg RAE, more than twice the adult UL. Check prenatal vitamin labels for the retinol share.
- Bones. Two large cohorts linked high retinol intake or high blood retinol to more hip fractures. EFSA reviewed the evidence in 2024. It concluded that cause cannot be established at intakes below the UL. It also found that the evidence does not support harm to bone at 3,000 mcg RE a day or less.
- Smokers and beta-carotene. High-dose beta-carotene raised lung cancer and deaths in smokers and asbestos-exposed workers in ATBC and CARET. Lung cancer was also higher with beta-carotene in AREDS2, mostly in former smokers. EFSA says smokers should avoid beta-carotene supplements. It found no indication that beta-carotene from the background diet is linked to harm.
- Drug interactions. Orlistat, a weight-loss drug, can lower absorption of vitamin A and beta-carotene, and its makers advise a multivitamin with vitamin A. Prescription retinoids such as acitretin and bexarotene can raise the risk of vitamin A toxicity when combined with vitamin A supplements. Some retinoid medicines, such as isotretinoin and etretinate, can cause birth defects, according to the NIH.
- Who should ask a doctor. Ask if you are or might be pregnant, or are breastfeeding. Experts advise these women not to take more than 3,000 mcg RAE (10,000 IU) of vitamin A a day as supplements. Also ask if you take retinoid medicines or orlistat, or if you smoke or used to smoke and are considering beta-carotene. People with macular degeneration should ask about their vitamin A intake and the AREDS formulas. People with cystic fibrosis or fat malabsorption often need vitamin A, and the amount belongs under medical care.
How to get more vitamin A
- Best foods. In our ranking, one medium sweet potato gives 1,188 mcg RAE and one medium carrot 509 mcg. For preformed vitamin A, the NIH lists a hard-boiled egg at 75 mcg. A cup of milk with added vitamin A and D has 149 mcg, and three ounces of pickled herring 219 mcg.
- Eat orange foods with some fat. A salad with full-fat dressing gave the most carotenoid absorption in one trial. The NIH says cooking can raise how much beta-carotene the body can use.
- Keep liver occasional. Three ounces of beef liver hold 6,582 mcg RAE. EFSA says the UL is unlikely to be passed if liver is eaten once a month or less, and advises against it in pregnancy.
Sources
- Vitamin A and carotenoids: fact sheet for health professionals. National Institutes of Health, Office of Dietary Supplements. Updated March 10, 2025.
- EFSA Panel on Nutrition, Novel Foods and Food Allergens (NDA). Scientific opinion on the tolerable upper intake level for preformed vitamin A and β-carotene. EFSA J. 2024.
- Imdad A, Mayo-Wilson E, Haykal MR, et al. Vitamin A supplementation for preventing morbidity and mortality in children from six months to five years of age. Cochrane Database Syst Rev. 2022.
- Rothman KJ, Moore LL, Singer MR, et al. Teratogenicity of high vitamin A intake. N Engl J Med. 1995.
- Feskanich D, Singh V, Willett WC, et al. Vitamin A intake and hip fractures among postmenopausal women. JAMA. 2002.
- Michaëlsson K, Lithell H, Vessby B, et al. Serum retinol levels and the risk of fracture. N Engl J Med. 2003.
- Cortés-Jofré M, Rueda JR, Asenjo-Lobos C, et al. Drugs for preventing lung cancer in healthy people. Cochrane Database Syst Rev. 2020.
- Brown MJ, Ferruzzi MG, Nguyen ML, et al. Carotenoid bioavailability is higher from salads ingested with full-fat than with fat-reduced salad dressings as measured with electrochemical detection. Am J Clin Nutr. 2004.
- Myhre AM, Carlsen MH, Bøhn SK, et al. Water-miscible, emulsified, and solid forms of retinol supplements are more toxic than oil-based preparations. Am J Clin Nutr. 2003.
- Costa CS, Bagatin E, Martimbianco ALC, et al. Oral isotretinoin for acne. Cochrane Database Syst Rev. 2018.
- Vahlquist A, Michaëlsson G, Juhlin L. Acne treatment with oral zinc and vitamin A: effects on the serum levels of zinc and retinol binding protein (RBP). Acta Derm Venereol. 1978.
- Alpha-Tocopherol, Beta Carotene Cancer Prevention Study Group. The effect of vitamin E and beta carotene on the incidence of lung cancer and other cancers in male smokers. N Engl J Med. 1994.
- Omenn GS, Goodman GE, Thornquist MD, et al. Effects of a combination of beta carotene and vitamin A on lung cancer and cardiovascular disease. N Engl J Med. 1996.
- Age-Related Eye Disease Study 2 Research Group. Lutein + zeaxanthin and omega-3 fatty acids for age-related macular degeneration: the Age-Related Eye Disease Study 2 (AREDS2) randomized clinical trial. JAMA. 2013.
History of vitamin A
People described the symptoms long before they knew the cause. Night blindness was recognized by the ancient Egyptians and Greeks, and many authorities from Galen onward advised liver as a cure.
In 1816, the physiologist François Magendie fed dogs a poor diet and saw corneal ulcers and high mortality. It was much like what happened to poorly fed, abandoned infants in Paris. In the 1880s, Nicolai Lunin showed that milk held an unknown substance that animals needed.
In 1913, two American teams reached the same conclusion. They were Elmer McCollum and Marguerite Davis at Wisconsin, and Thomas Osborne and Lafayette Mendel at Yale. Butter and egg yolk helped rats grow and survive better than lard and olive oil. The growth factor became known as “fat-soluble A” in 1918 and as “vitamin A” in 1920.
During World War I, Bloch ran a controlled diet trial among malnourished Danish children. Bloch concluded that whole milk, butter and cod-liver oil contain a fat-soluble substance that protects against xerophthalmia.
Chemistry followed. Paul Karrer described the structure of vitamin A in 1932, and Harry Holmes and Ruth Corbet isolated and crystallized it in 1937. Methods to make it in the lab came in 1946 and 1947. From the 1930s, George Wald and colleagues worked out how vitamin A powers vision.
Large trials in the 1980s and 1990s reported marked drops in child deaths from vitamin A supplements. Later, larger trials found smaller or no effects. The pooled result in the latest Cochrane review is a 12% reduction in deaths from any cause.
Sources
- Semba RD. On the ‘discovery’ of vitamin A. Ann Nutr Metab. 2012.
- Lanska DJ. Chapter 29: historical aspects of the major neurological vitamin deficiency disorders: overview and fat-soluble vitamin A. Handb Clin Neurol. 2010.
- Imdad A, Mayo-Wilson E, Haykal MR, et al. Vitamin A supplementation for preventing morbidity and mortality in children from six months to five years of age. Cochrane Database Syst Rev. 2022.
Frequently asked questions about vitamin A
Is beta-carotene the same as vitamin A?
No. Beta-carotene is a plant pigment that the body converts into vitamin A in the intestine, according to the NIH. It counts toward vitamin A at an exchange rate. In the US, 12 mcg of beta-carotene from food equals 1 mcg RAE, and so do 2 mcg from supplements. Preformed vitamin A (retinol) comes from animal foods and supplements. The difference matters for safety. Beta-carotene is not known to cause birth defects, and its usual long-term effect is harmless yellow-orange skin. But high-dose beta-carotene pills raised lung cancer in smokers in ATBC and CARET.
Are vitamin A and retinol the same?
Not quite. Retinol is the main preformed form of vitamin A. Vitamin A is the group name for fat-soluble retinoids, mainly retinol and retinyl esters. Labels give vitamin A in mcg RAE so forms can be compared (1 mcg retinol equals 1 mcg RAE). Prescription retinoids such as isotretinoin, acitretin and bexarotene are drugs related to vitamin A, not supplements. The NIH says they can raise toxicity risk when combined with vitamin A supplements.
Can you get too much vitamin A from carrots?
Not toxic vitamin A. The NIH says the most common effect of long-term excess beta-carotene is carotenodermia, a harmless yellow-orange skin color that fades when intake stops. Beta-carotene is not known to cause birth defects or reproductive toxicity. Toxicity comes from preformed vitamin A in liver and supplements. The exception to watch is large beta-carotene supplements in smokers.
Is vitamin A safe in pregnancy?
At recommended amounts, yes. Needs rise slightly, to 770 mcg RAE a day in the US at ages 19 to 50, or 700 mcg RE in the EU. Preformed vitamin A above the 3,000 mcg upper limit can cause birth defects. In one cohort, the rate of certain defects was 4.8 times higher above 10,000 IU a day of supplemental vitamin A. The excess was mostly before the seventh week. EFSA advises women who are pregnant or planning to be not to eat liver products. Check prenatal vitamin labels for the retinol share and ask a midwife or doctor.
Which foods are highest in vitamin A?
In our USDA ranking per serving, sweet potatoes lead with 1,188 mcg RAE in one medium potato. Carrots (509 mcg), cantaloupe (270 mcg per cup), bell peppers (187 mcg) and garden cress (173 mcg) follow. Per 100 g, carrots (835 mcg) and sweet potatoes (787 mcg) lead. Liver is higher than all of them but is not in our ranking. The NIH lists 6,582 mcg RAE in 3 ounces of pan-fried beef liver.
Does cooking destroy vitamin A?
Cooking can raise how much beta-carotene you absorb. The NIH says cooking and heat treatment can increase the bioavailability of beta-carotene (how much your body can absorb and use). In one trial, breaking up the cell walls of spinach raised beta-carotene absorption from 5.1% to 9.5% relative to a supplement. A review of food science says the main cause of loss in processing and storage is oxidation, helped by oxygen, light and long storage. We found no loss figure for retinol in cooking.
Does vitamin A help acne?
Vitamin A from food or ordinary supplements has not been shown to treat acne. Prescription retinoids are the acne treatments. A Cochrane review of 31 trials in 3,836 people found low-quality evidence on them. Against oral antibiotics plus skin treatments, oral isotretinoin may slightly improve doctor-rated severity (1.15 times) but caused more minor side effects (1.67 times). The NIH says retinoid medicines can cause birth defects. The only trial of oral vitamin A for acne we found, from 1978, reported blood levels of zinc and retinol-binding protein, not skin results.
Does vitamin A improve eyesight?
Only if you are short of it. Vitamin A is part of rhodopsin, and night blindness is the first sign of deficiency. In the Cochrane review of children, supplements cut night blindness (0.32 times the risk), mostly in places where deficiency is common. The EU authorizes the claim that vitamin A contributes to the maintenance of normal vision. In the studies on this page, we found no trial showing that extra vitamin A improves sight in people who already have enough. The macular degeneration trials used a mix of nutrients.